What it is
A regulated health professional who cares for you through pregnancy, birth, and the postpartum period.
A regulated healthcare professional providing care during pregnancy, labor, delivery, and postpartum.
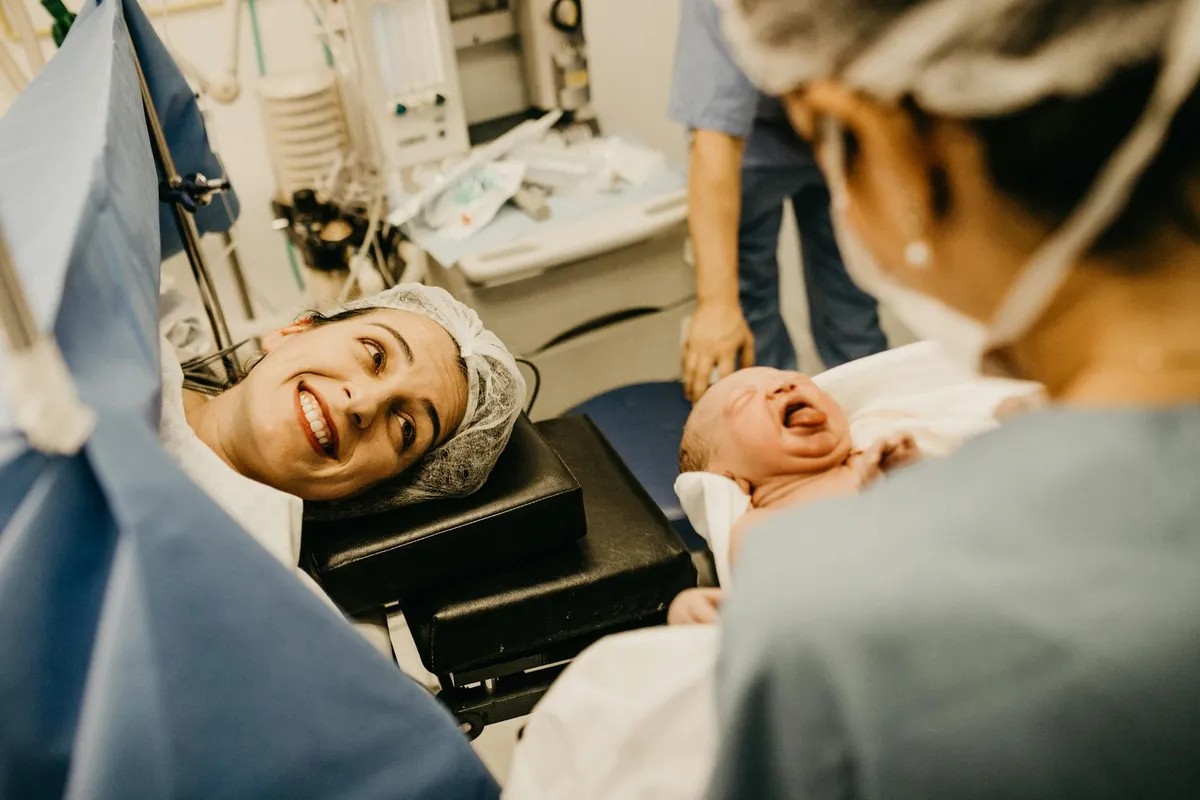
At a glance
What it is
A regulated health professional who cares for you through pregnancy, birth, and the postpartum period.
Why explore it
People choose one for personal birth planning and continuity of care in low-risk pregnancies.
How it’s experienced
A 60 to 90 minute first visit covering health history, an exam, and your birth preferences.
Evidence context
Research supports midwife-attended care for low-risk pregnancies, with safe outcomes.
See the evidence snapshotSafety
Best for low-risk pregnancies. Complex medical conditions need a doctor's input.
See staying safeHistory & Origin
A licensed midwife is a regulated health professional who provides care during pregnancy, birth, and the weeks afterward. They focus on healthy, low-risk pregnancies and offer a continuous relationship, so the same person who knows your history is often with you through labor and postpartum.
Working with a midwife usually begins with a longer first visit of about 60 to 90 minutes, covering your health history, a physical exam, baseline lab tests, and your hopes for birth. Visits continue through pregnancy with education and planning. Care often extends to labor support, newborn checks, and help with feeding.
People choose a midwife for personalized birth planning, steady companionship during labor, and postpartum support, including breastfeeding help. A midwife also coordinates with physicians when more medical expertise is needed, which is part of safe practice rather than a sign that something has gone wrong.
The evidence is strong for the role midwives play. Large cohort studies and clinical trials find that, for low-risk pregnancies, midwife-led care is associated with outcomes comparable to or better than physician-led care, along with fewer routine interventions. Risk assessment matters, and results depend on the setting and the person's health.
People with significant existing conditions, such as hypertension, diabetes, heart disease, or autoimmune disorders, should speak with a physician early, and many can be co-managed. Choose a midwife licensed in your state or region, and ask about their emergency protocols and how they arrange hospital transfer if it is needed.
Midwifery is among the oldest forms of care, with skilled birth attendants documented in many cultures. In the United States, formal training developed in the early twentieth century. Mary Breckinridge founded the Kentucky Committee for Mothers and Babies in 1925, later renamed the Frontier Nursing Service, bringing nurse-midwives trained in Britain to rural Leslie County, and she established a school of midwifery in 1939, which is now Frontier Nursing University.
The American College of Nurse-Midwives, founded in 1955, defines the nurse-midwife pathway, and certified nurse-midwives are registered nurses with graduate education. A separate pathway exists for direct-entry midwives. The North American Registry of Midwives created the Certified Professional Midwife credential in 1994, and California established the title licensed midwife in 1993 under its Licensed Midwifery Practice Act. The term licensed midwife therefore refers to a state license, and its scope and requirements differ by state.
Across the world, midwives are recognized as primary providers for healthy, low-risk pregnancy and birth. In the US, rules about where they may practice, which medications they may carry, and how they collaborate with physicians are set by each state. Anyone seeking a midwife should verify the license and credentials in the relevant state.
Mechanism
A licensed midwife is a regulated professional who combines clinical assessment with ongoing support, and works with physicians when a pregnancy needs more medical expertise.
Your first visit
A typical session outline to help you feel prepared
Practices differ, but a first visit with a licensed midwife often follows a shape like the one below. You can ask about any step before you book.
You can ask about the midwife's license, training, and the settings where she attends births, and she explains how care will run.
The midwife reviews your medical records, past pregnancies, medications, and family history, usually over a longer first visit.
Each exam or test is explained first, and you decide what to accept, with the option to pause or decline.
The visit may include vital signs, a physical exam, and baseline lab work such as blood type and anemia screening.
Together you review whether your pregnancy suits midwife-led care and which conditions would call for a physician.
You talk about your birth preferences, and the midwife outlines the visit schedule and how to reach her between appointments.
The visit ends with your questions, a plan for follow-up, and a reminder that midwifery works alongside medical care.
The evidence
An honest read on how Licensed Midwife has been studied — an evidence tier and the research behind it, not a guarantee and not a ranking of “better.”
Among the more studied approaches
Licensed Midwives practice within a well-established evidence-based framework with decades of clinical research supporting safe, effective prenatal care and labor management for low-risk pregnancies.
Evidence is strong for low-risk pregnancies.
Evidence is strongest for low-risk pregnancies; higher-risk care needs coordination with physicians and medical care.
Safety first
General guidance to help you decide whether this approach is appropriate for you. This is informational only and not a substitute for medical, psychological, or professional advice.
If you are pregnant, managing a health condition, recovering from injury or surgery, or taking medication, consult a qualified healthcare professional first.
Some situations call for extra care or a different approach. Share any conditions, injuries, or sensitivities with your practitioner before your first session.
Look for clear boundaries, transparent pricing, and practitioners who avoid fear-based claims or pressure to book frequent sessions.
Mild, short-lived effects such as tenderness, tiredness, or temporary soreness can occur. Rest, hydrate, and tell your practitioner how you respond.
For you?
A simple, human way to weigh it up. This is general guidance, not personal medical advice — a qualified practitioner can advise on your situation.
Gyfts is a discovery platform, not a medical provider. Nothing here diagnoses, treats or replaces professional care. In an emergency, contact your local emergency number.
In their words
Before you book
FAQ
A Certified Nurse-Midwife (CNM) is a registered nurse who has completed additional graduate-level education in midwifery and passed national certification. A Licensed Midwife (LM) may have different educational pathways depending on the state and may not be a nurse; requirements vary significantly by jurisdiction. Both are regulated healthcare providers, but credentials and scope of practice differ by state. Always verify your provider's specific licensure and credentials.
Many Licensed Midwives are trained to provide prenatal care and monitoring for certain high-risk conditions (gestational diabetes, mild hypertension) in collaboration with an obstetrician. However, some conditions require physician-led primary care. The key is clear communication with your midwife about your specific health situation and establishment of collaborative relationships with physicians when needed.
Standard prenatal care typically includes 14 to 16 visits over a 40-week pregnancy: roughly monthly visits in the first two trimesters, every 2 to 3 weeks in the third trimester, and weekly visits near term. Additional visits may be needed for specific concerns. Your individual schedule may vary based on risk factors and preferences.
Licensed Midwives are trained to recognize complications and initiate appropriate responses, which typically includes notifying the obstetric team, transferring to hospital care if necessary, and ensuring seamless transition of care. Complications such as fetal distress, excessive bleeding, or maternal vital sign changes prompt immediate intervention and physician consultation. Discuss transfer protocols and emergency procedures with your midwife before labor.
This depends on your practice setting. Midwives working in hospitals typically have access to all pain management options including epidural, IV pain medication, and nitrous oxide. Midwives in birth centers may offer nonpharmacologic options (position changes, water immersion, breathing) and sometimes oral or intramuscular medications, with hospital transfer available for epidural if desired. Discuss available options during your prenatal care.
Postpartum care typically includes physical assessment (bleeding, wound healing, vital signs), emotional health screening for postpartum depression, breastfeeding support, newborn feeding and care guidance, and family planning counseling. Many midwives offer extended postpartum visits at 12 weeks or longer. Some provide lactation consultation, perineal care instruction, and ongoing primary care coordination.
Coverage depends on your insurance plan and whether your midwife is in-network. Certified Nurse-Midwives (CNMs) are typically covered by most insurance plans; Licensed Midwives (LMs) coverage varies by state and insurer. Some insurance plans cover hospital-based midwifery but not birth center care. Verify coverage with your insurance company and discuss costs and payment options with your midwife's office.
References
Educational sources that inform this overview. Inclusion is for context and does not imply endorsement.
Full citations are maintained by the Gyfts editorial team and reviewed periodically.
Keep exploring
Browse practitioners, explore honest overviews, and take what you learn to a conversation — at your own pace.

